
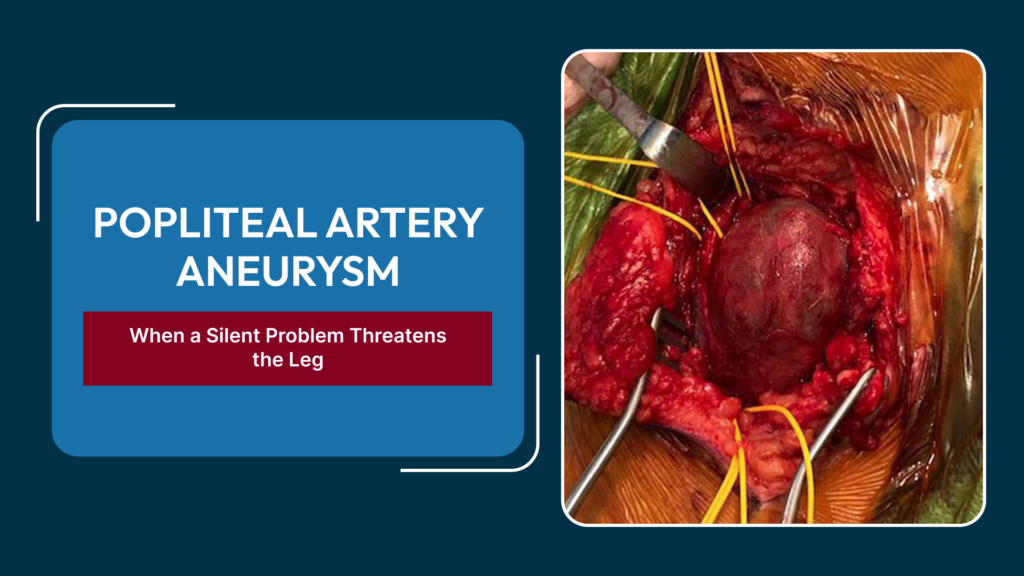
The popliteal artery, running behind the knee, is the most common site of a peripheral artery aneurysm — an abnormal, permanent widening of the vessel wall. Unlike an abdominal aortic aneurysm, where the main danger is rupture, a popliteal artery aneurysm (PAA) more often threatens the leg through blood clot formation inside the bulging segment, which can suddenly block flow to the foot. Because it frequently causes no symptoms until a complication occurs, a vascular surgeon in Delhi looks for it deliberately in at-risk patients rather than waiting for it to announce itself.
What a Popliteal Artery Aneurysm Is
A popliteal artery is generally considered aneurysmal when its diameter exceeds about 1.5 times the normal adjacent vessel, though many surgeons use an absolute diameter of around 2 centimeters as a practical threshold. The aneurysm develops in the segment of artery running through the popliteal fossa behind the knee joint. Popliteal aneurysms are bilateral — present in both legs — in a substantial proportion of patients, and are strongly associated with abdominal aortic aneurysms, which are present in a significant minority of people diagnosed with a PAA.
Why It’s Dangerous in a Different Way Than Other Aneurysms
Rupture, the feared complication of an abdominal aortic aneurysm, is comparatively uncommon with popliteal aneurysms. The greater threat is that blood flow inside the widened, turbulent segment slows and clots, either blocking the artery outright (thrombosis) or breaking off in fragments that lodge in the smaller arteries further down the leg (distal embolization). Either process can produce sudden, severe limb ischemia, and because the popliteal artery has limited natural collateral pathways compared with some other vessels, an acute blockage here carries a real risk of limb loss if not treated promptly.
Risk Factors and Associations
- Popliteal aneurysms occur far more often in men than women
- Advancing age and a history of smoking increase risk
- Generalized atherosclerosis is commonly present alongside the aneurysm
- A significant proportion of patients also have an abdominal aortic aneurysm, warranting screening of the aorta
- The condition is bilateral in a substantial share of cases, so the opposite knee is always checked
Symptoms and How It’s Found
Many popliteal aneurysms are discovered incidentally, on imaging done for another reason or during a routine pulse examination that reveals a prominent, pulsatile mass behind the knee. When they do cause symptoms, patients may notice calf pain or swelling from compression of the adjacent popliteal vein or nerve, cramping on walking, or the sudden onset of a cold, painful, numb foot if the aneurysm has thrombosed or embolized — a presentation that is a vascular emergency.
Diagnosis
Duplex ultrasound is the standard first test, confirming the aneurysm’s size and detecting any thrombus inside it non-invasively. Once a repair is being planned, CT or MR angiography maps the artery’s full length, the run-off vessels below the knee, and the condition of the opposite leg and the aorta, all of which influence the treatment plan.
When Treatment Is Needed
Because the main risk with a PAA is thromboembolism rather than rupture, treatment thresholds are lower than for an abdominal aortic aneurysm of similar size — many vascular surgeons recommend repair once the diameter reaches roughly 2 centimeters, particularly if thrombus is visible within the sac, even in the absence of symptoms. Any patient with symptoms — claudication, compression symptoms, or acute limb ischemia — is treated regardless of the exact measurement, since the risk of a limb-threatening event outweighs watchful waiting at that point.
Treatment Options
Open surgical repair — ligating the aneurysm and bypassing it with a graft, ideally using the patient’s own vein — has long been the standard approach and offers durable results, particularly when good-quality vein is available and the patient is fit for surgery. Endovascular repair, placing a covered stent graft across the aneurysm from within the artery, offers a less invasive alternative with a shorter recovery and is often favored in patients with higher surgical risk or anatomy suited to a stent graft, though long-term durability data continues to be compared against open repair. The choice between the two depends on the aneurysm’s anatomy, the condition of the run-off vessels, and the patient’s overall fitness.
Follow-Up After Diagnosis or Treatment
Given the strong association with aortic aneurysms and the tendency toward bilateral disease, patients diagnosed with a popliteal aneurysm are typically screened for an abdominal aortic aneurysm and have the opposite knee assessed as well. After repair, periodic imaging checks graft patency and watches for aneurysmal change developing in the other leg over time.
How It’s Different From a Baker’s Cyst or Other Knee Lumps
A pulsatile mass behind the knee is sometimes mistaken for other common causes of a knee-area lump, such as a Baker’s cyst, which is a fluid-filled swelling rather than a vascular structure and does not pulsate with the heartbeat. The key distinguishing feature on examination is that a popliteal aneurysm expands and pulses in time with the pulse, while a cyst does not — but because this distinction is not always obvious on physical exam alone, any new lump behind the knee, especially in an older patient with vascular risk factors, is reasonably evaluated with ultrasound to rule an aneurysm in or out before assuming it is something more benign.
Why Screening Matters Even Without Symptoms
Because a popliteal aneurysm can remain silent for years before a thromboembolic event brings a patient in with an acutely ischemic leg, screening in higher-risk groups — older men, smokers, and anyone already known to have an abdominal aortic aneurysm — is one of the few ways to catch the condition before it causes an emergency. A brief pulse examination and, where indicated, an ultrasound scan are low-burden ways to identify an aneurysm while it is still an elective, planned problem rather than a limb-threatening one.
Frequently Asked Questions
Can a popliteal artery aneurysm be felt during a routine check-up?
Often yes — an experienced examiner can sometimes feel an unusually prominent, bounding pulse behind the knee, though many aneurysms are only confirmed with ultrasound.
Is a popliteal aneurysm as dangerous as an abdominal aortic aneurysm?
It carries a different kind of danger — rupture is comparatively uncommon, but the risk of sudden limb-threatening clotting or embolization is significant, which is why treatment thresholds focus on that risk rather than rupture risk.
If I have a popliteal aneurysm, should my other leg be checked?
Yes, popliteal aneurysms are frequently present in both legs, so the opposite side is routinely examined and imaged once one side is diagnosed.
Does having a popliteal aneurysm mean I need my aorta checked too?
Given the strong association between the two conditions, most vascular surgeons recommend screening the abdominal aorta in anyone diagnosed with a popliteal artery aneurysm.
Is surgery always needed once a popliteal aneurysm is found?
Not immediately — smaller, asymptomatic aneurysms without visible clot may be monitored with periodic ultrasound, while larger aneurysms, those with thrombus, or any symptomatic aneurysm are generally recommended for repair.
A pulsatile lump behind the knee or a sudden cold, painful foot both deserve prompt vascular evaluation. Find answers to common questions at our vascular surgery FAQs

